Piles (Hemorrhoids): Symptoms and Treatment Options
Piles are enlarged, cushion-like veins at the anus — extremely common, often manageable without surgery, but sometimes needing a procedure. This guide explains the grades, what each treatment actually does, and the signs that mean you should be seen.
📞 87478 74666 💬 WhatsApp UsDhaara Speciality Hospital, Yelahanka
61 Jakkur Road, Yelahanka, Bengaluru 560064
24/7
Emergency Care
Insurance & cashless
Treatment support
Key Takeaways
- Piles are normal anal cushions that have become enlarged — grade I stays inside, grade IV stays outside.
- Fibre, fluids and avoiding straining control most grade I–II piles without any procedure.
- Painless bright-red bleeding is typical of piles — but bleeding with changed bowel habit, weight loss or dark blood must be investigated to rule out colonic causes.
- Office procedures (banding, sclerotherapy) and surgeries (haemorrhoidectomy, stapled, artery embolisation) are graded to match severity.
- Persistent bleeding, prolapse you cannot reduce, severe pain or a lump with fever all deserve same-week assessment.
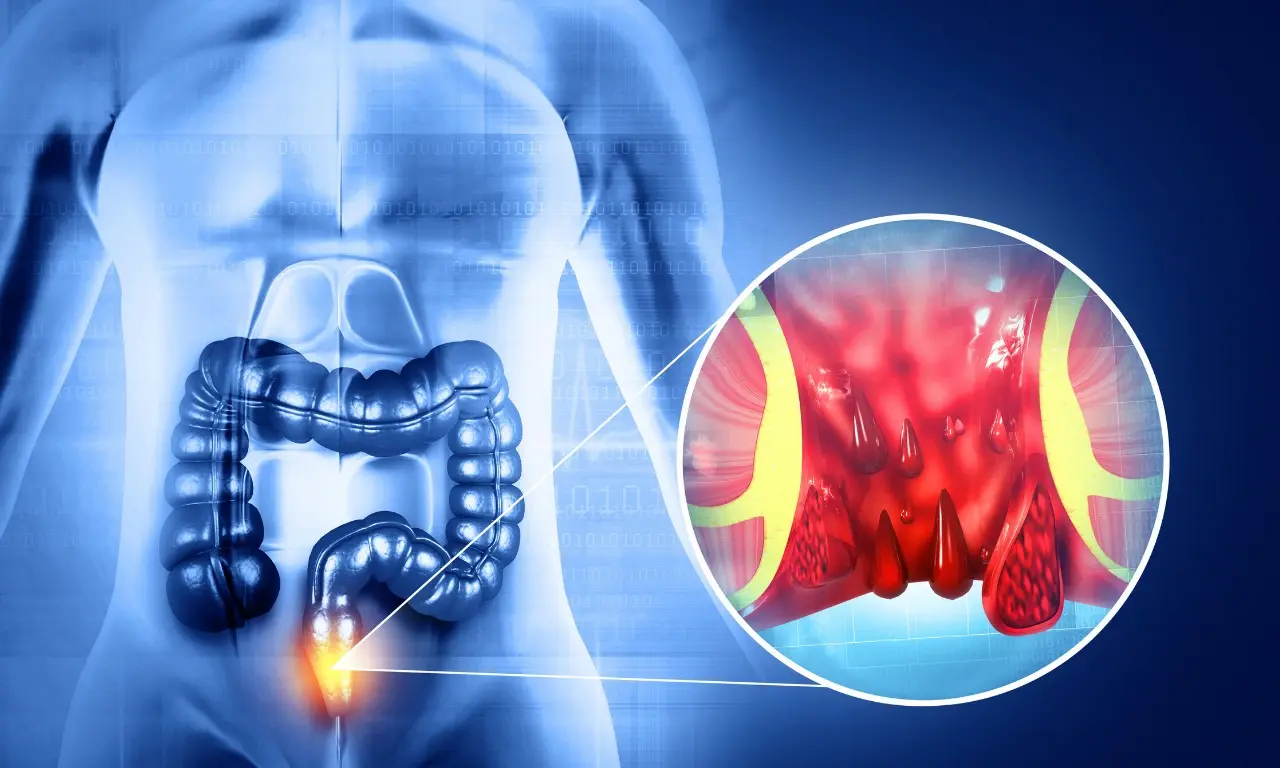
Nearly half of adults get piles. Piles are hemorrhoids. Pregnancy causes piles. Chronic constipation causes piles. Sitting long on the toilet causes piles. Heavy lifting causes piles. Getting older causes piles. These things enlarge anal cushions. Anal cushions are natural body parts. Enlarged cushions cause symptoms. Symptoms include painless bleeding. Symptoms include itching. Symptoms include discomfort. Symptoms include a lump. The lump slides out during bowel movements. Most piles need lifestyle changes. Lifestyle changes can manage piles. Treatments exist for piles. Treatments are simple. Treatments are comfortable. Treatments are better than feared.
The Four Grades — Why They Matter
| Grade | What happens | Usual approach |
|---|---|---|
| I | Swollen cushions bleed or itch but never come out | Diet, fibre, sitz baths, creams for short courses |
| II | Come out during passing stool, go back on their own | Lifestyle measures; banding if troublesome |
| III | Come out and need a finger to push back | Usually a procedure — banding, surgery or embolisation |
| IV | Stay out permanently and cannot be pushed back | Surgery is generally the definitive option |
Grading drives treatment. A grade I pile bleeds twice a month. It often needs nothing. Just eat fibre. Fix toilet habits. A grade IV pile stays outside. It is permanent. It will keep troubling you. It happens no matter what you eat.
What You Can Do at Home (Genuinely Works for Early Piles)
- 25–30 g fibre daily — vegetables, whole grains, fruits; a soft bulky stool is the single most effective treatment.
- 2–3 litres of fluid a day — fibre without water hardens stool.
- No straining, no reading on the toilet — keep toilet time under 5 minutes; prolonged sitting engorges the cushions.
- Warm sitz baths — 10–15 minutes, twice a day, ease discomfort during flare-ups.
- Short courses of pharmacy creams/suppositories — useful for a flare, but not for months at a time; prolonged steroid creams thin the skin.
When Home Care Is Not Enough
See a surgeon if bleeding lasts past a couple of weeks. See a surgeon if the lump prolapses. This is grade III-IV. Go if pain is severe. A thrombosed pile is a clotted one. It can be extremely painful. This pain lasts for days. Go if any red flags appear.
Red Flags — Get Assessed, Don't Assume It's "Just Piles"
- Bleeding with a change in bowel habit (new constipation or loose stools lasting weeks).
- Dark or mixed-in blood (rather than bright red on the surface or paper).
- Unexplained weight loss, fatigue or anaemia.
- A painful lump with fever — that pattern suggests an abscess, not piles (see our fistula guide).
Rectal bleeding needs a check. It always needs one proper exam. A short clinical exam is good. A colonoscopy may be needed. This gives you certainty. Reassurance is worth the visit.
Treatment Options, Simplest to Definitive
- Lifestyle measures — as above; the foundation for every grade.
- Band ligation (office procedure) — a small rubber band cuts off the pile's blood supply; takes minutes in clinic, no cutting. Suited to grade I–III.
- Sclerotherapy / injection — a solution shrinks small bleeding piles; often combined with banding.
- Haemorrhoidectomy — surgical removal, the most definitive treatment for grade III–IV; modern techniques and good pain protocols make recovery very manageable (typically 1–2 weeks of soreness).
- Stapled haemorrhoidopexy — circles the prolapsing cushions back inside; less wound pain than excision for suitable patients.
- Hemorrhoidal artery embolisation — a radiology-guided day-care option that blocks the feeding arteries; an alternative for patients who want to avoid or cannot undergo surgery. Our haemorrhoids treatment page covers this in detail.
There is no best treatment. Your grade matters. Your symptoms matter. Your health matters. Doctors decide at a visit. They do not pick from a menu. Our general surgery team helps you. They check anorectal conditions daily. They treat them daily.
Frequently Asked Questions
Talk to Dhaara — reachable 24×7
Call 9am?9pm within 2 minutes. After hours, every WhatsApp lands in our staff queue with an auto-callback.
📞 87478 74666 💬 WhatsApp UsTreatment & Procedure Pages
Laparoscopic Cholecystectomy in Yelahanka
Keyhole gallbladder removal at Dhaara — day-care protocol, recovery timeline and surgeon profile.
Appendix Surgery (Appendectomy)
Emergency laparoscopic appendectomy in Yelahanka — warning signs, surgery and recovery.
GERD & Nissen Fundoplication
Acid reflux care in Yelahanka — from medical therapy to laparoscopic Nissen fundoplication.
Related Patient Guides
Anal Fistula
Why the tunnel keeps refilling, and how surgery chooses cure vs sphincter safety.
Anal Fissure
The pain-spasm cycle, healing at home and when surgery is the kinder option.
Get help before your op
Symptoms, preparation, recovery and warning signs — explained simply.

.webp)
.webp)

