If heartburn has become your nightly companion — or a tablet has become your breakfast — this page was written for you. Together we will walk through why reflux happens, when it becomes a disease, how it is investigated and controlled, and when surgery offers a lasting cure at Dhaara Speciality Hospital, Yelahanka.
Medically reviewed by Dr. Srinivas Bojanapu · September 2026
10,000+
Patients Treated
15+ Years
Surgical Experience
24/7
Emergency Care
GERD in 30 seconds
- What it is: stomach acid flowing backwards into your food pipe — because the valve at its lower end has weakened.
- Key symptoms: heartburn after meals and acid regurgitation — plus surprisingly different ones: chronic night cough, hoarseness, even dental erosion.
- Why it matters: reflux twice a week or more is a disease, not a nuisance — long-standing untreated GERD can cause strictures, Barrett's oesophagus and cancer.
- If you are worried: most patients improve hugely with structured lifestyle change and a defined medicine course.
- The good news: for those who cannot stay off medicines, keyhole surgery (fundoplication) offers a durable cure — 90–95% symptom-free at 10 years.
Why acid reflux keeps coming back — the mechanism
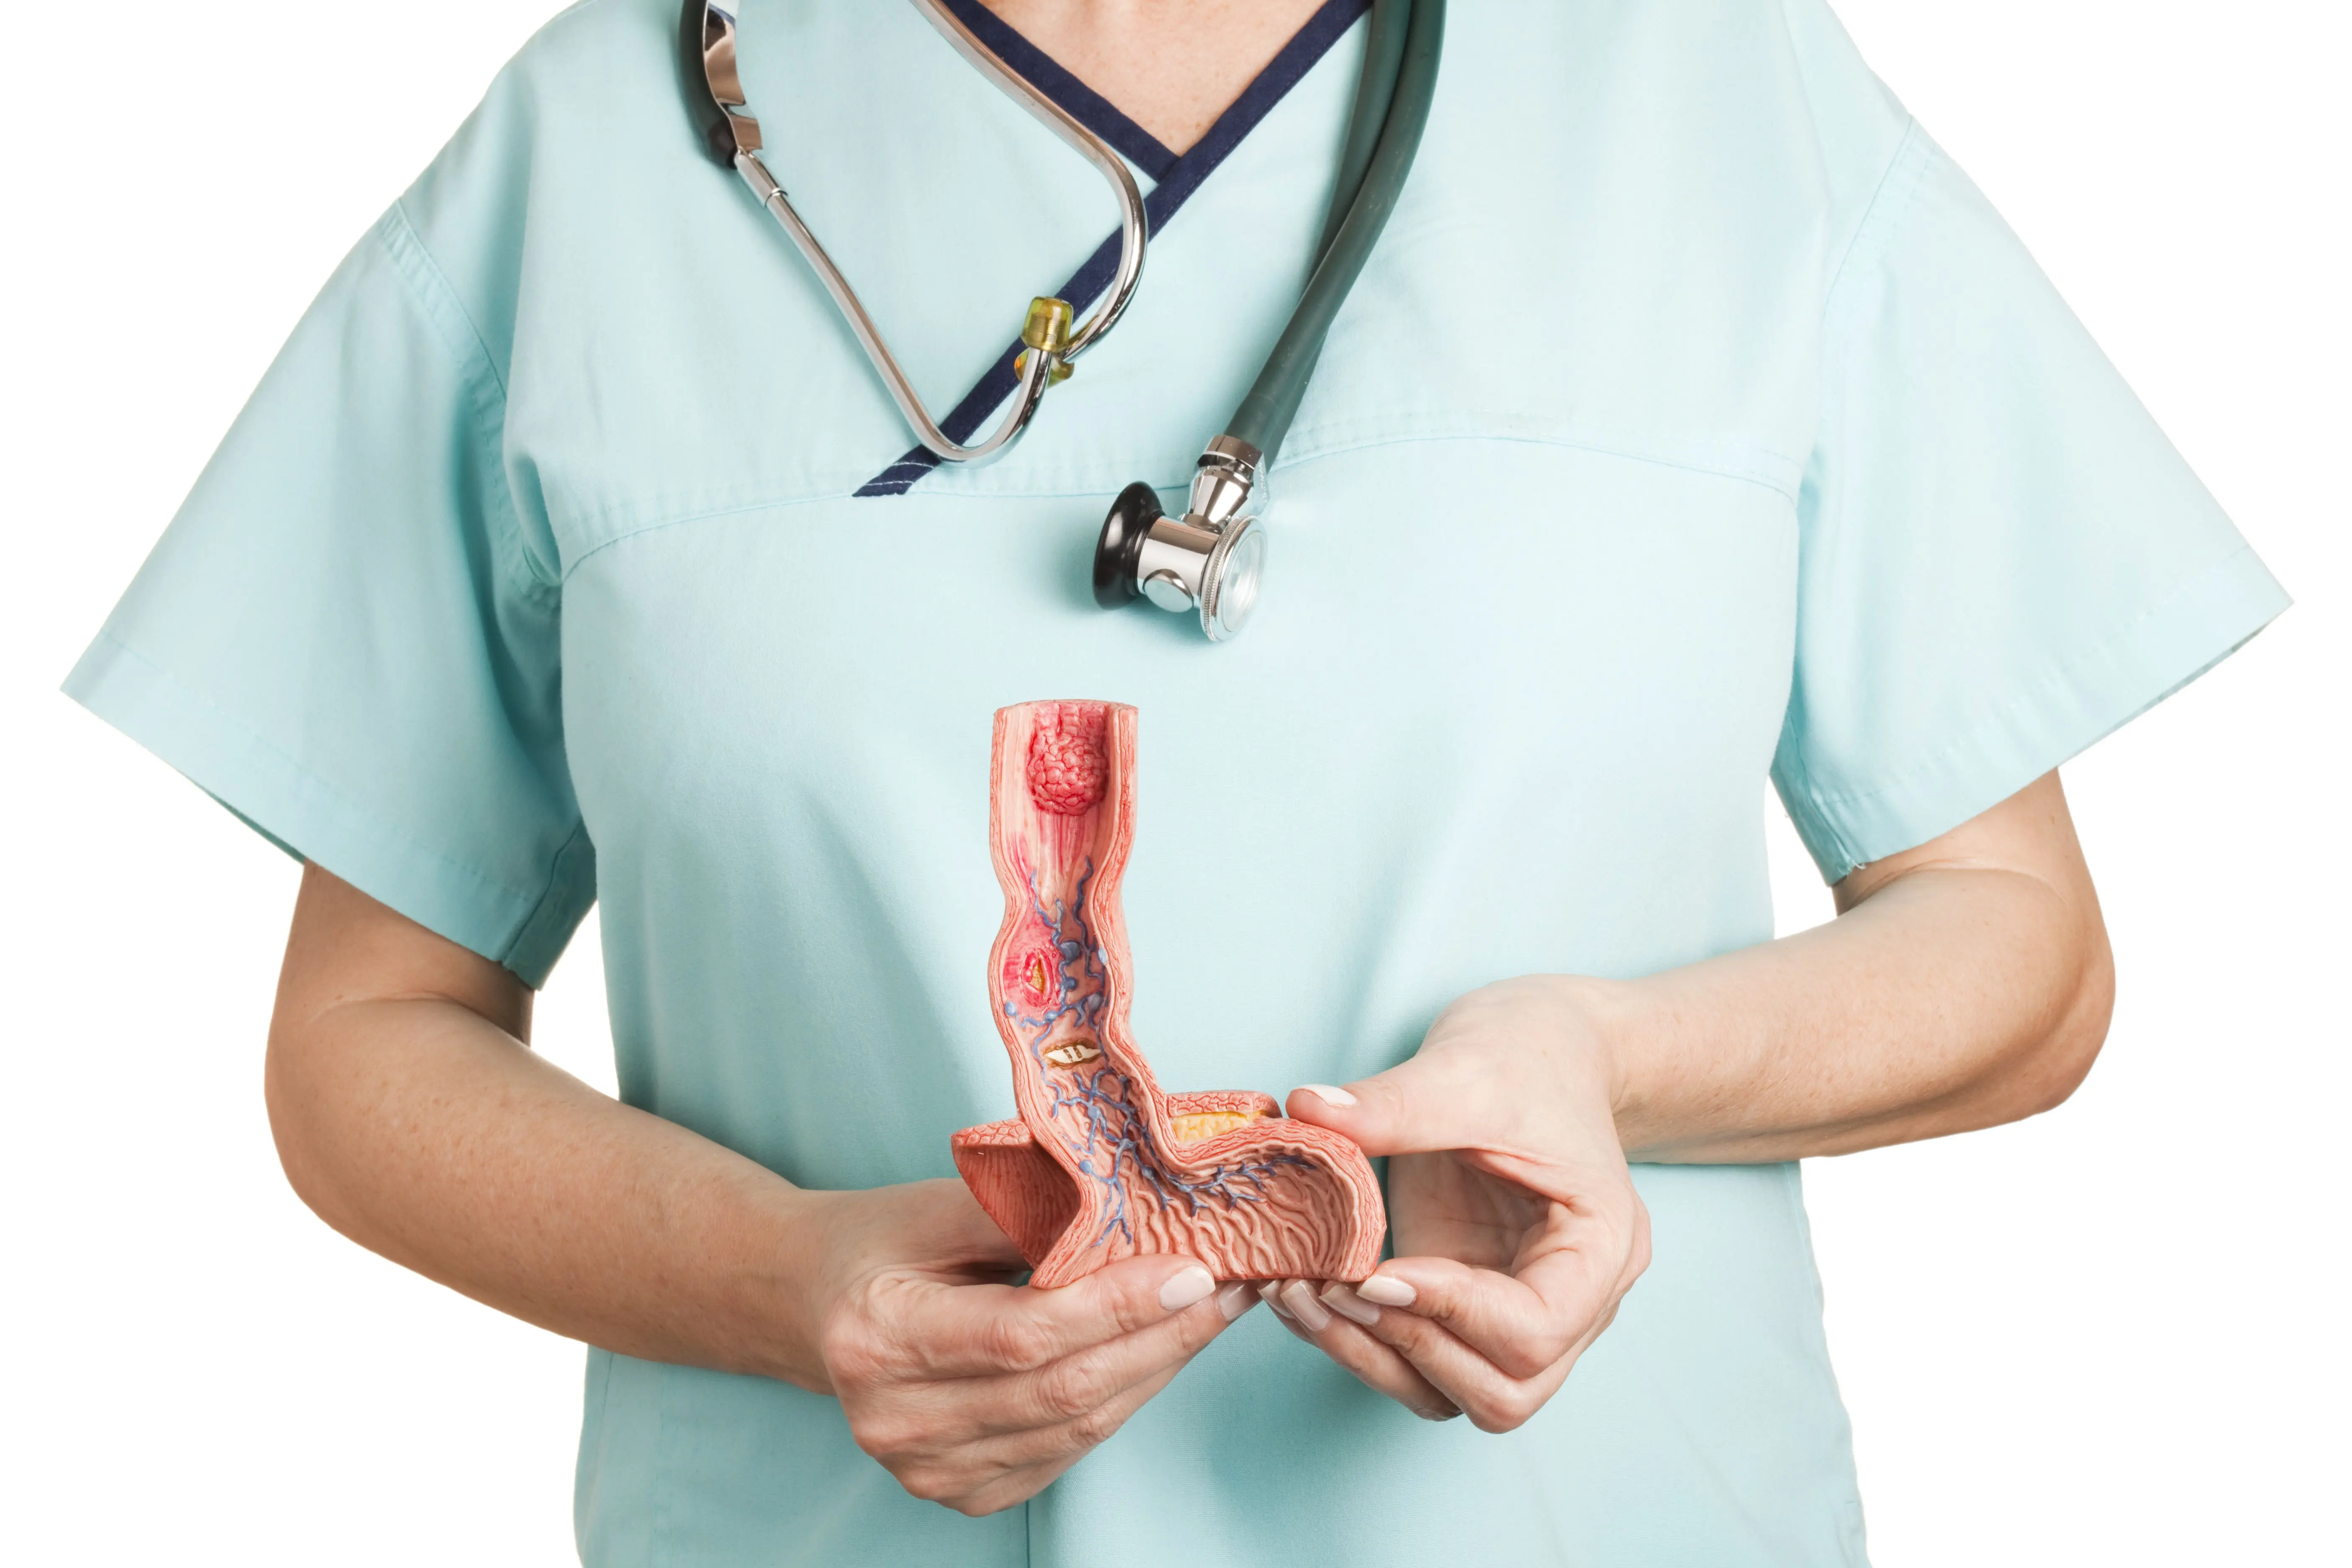
Here is the physics of it. At the lower end of your food pipe sits a muscular valve — the lower oesophageal sphincter — backed by the diaphragm's pinch as it crosses the chest. Together they are a one-way gate: food in, acid stays down.
Reflux is that gate failing — opened by obesity, a hiatus hernia, large or fatty meals, late-night eating, smoking, or simply years of pressure. And this single mechanism explains the great frustration of the disease: tablets neutralise the acid, but they do not repair the valve. That is why reflux keeps returning the moment the medicine stops — and why the plan on this page works on both sides: the acid and the gate.
What is GERD — and when is it not "just heartburn"?
Gastroesophageal reflux disease is a chronic condition: stomach acid flowing back into the oesophagus often enough to inflame it. The dividing line is frequency — twice a week or more, or any damage already visible on endoscopy. India has a rapidly rising prevalence, now affecting an estimated 18–30% of urban adults, linked to changing diets, obesity, stress and late eating. Occasional heartburn after a heavy biryani is not GERD; a weekly pattern that owns your evenings is.
Symptoms of GERD
Typical
- Heartburn — burning in the chest after meals
- Acid regurgitation — sour or bitter taste in the mouth
- Chest pain (non-cardiac)
- Worse lying down or bending over
Atypical — often missed
- Chronic cough, especially at night
- Hoarseness, sore throat, laryngitis
- Asthma worsening at night
- Dental erosions; lump-in-throat sensation (globus)
Red flags — endoscopy urgently
- Difficulty swallowing
- Weight loss
- Vomiting blood or black tarry stools
- Anaemia; symptoms not responding to antacids
Easily confused with
- Heart disease — chest pain must be cardiac-cleared first
- Gastritis and ulcers (see our gastritis page)
- Gallstones
- Chronic cough from lung causes
When should you see a doctor?
review
Next available appointment: heartburn twice or more a week; regular antacid use; symptoms you have simply learned to live with.
(days)
Within days: symptoms despite antacids or a medicine course; night cough or hoarseness without a cold; years of PPI dependence without ever having had an endoscopy.
(same day)
Do not wait: difficulty swallowing, weight loss, vomiting blood, black stools. And chest pain — rule out the heart first, always. Call 87478 74666; when in doubt, go to an emergency room.
What untreated reflux does over the years
The reason this disease deserves respect — a slow sequence, each stage preventable by treating the one before it:
| Stage | What happens | What it feels like |
|---|---|---|
| Oesophagitis | Erosions and ulcers in the oesophageal lining | Painful swallowing |
| Stricture | Scarring narrows the food pipe | Progressive difficulty swallowing |
| Barrett's oesophagus | Lining replaced by intestinal-type tissue — precancerous | Usually silent — found on endoscopy, needs surveillance |
| Oesophageal adenocarcinoma | Barrett's → dysplasia → cancer, in a minority | The reason surveillance exists |
For perspective: only ~0.3% of Barrett's patients develop cancer per year — this is a managed pathway, not a doom. Every stage above is treatable; the earlier the stage, the simpler the treatment.
How is GERD diagnosed? A step-by-step journey
- Clinical assessment. Pattern, frequency, triggers, medicines — and ruling out the heart whenever chest pain is involved.
- Trial of therapy. Typical, uncomplicated symptoms may start with structured lifestyle change and a defined PPI course.
- Upper GI endoscopy — documents the damage. Grades oesophagitis (LA Grade A–D), detects strictures and Barrett's, and biopsies anything suspicious. See endoscopy.
- 24-hour pH-impedance monitoring — where needed. The gold standard: it measures actual acid exposure over a full day and matches symptoms to reflux episodes.
- Oesophageal manometry — before any surgery. Measures the valve's pressure and the food pipe's movement; no anti-reflux operation is planned without it.
- Barium swallow — selectively. Useful for hiatus hernia and strictures.
Treatment — a three-step ladder
Step 1: Fix the mechanics
What: weight loss if overweight (BMI above 25 significantly worsens GERD), head-of-bed elevation 15–20 cm, no eating within 3 hours of bedtime, smaller meals, trigger avoidance (coffee, alcohol, spicy and fried food, chocolate, mint, citrus), quitting smoking. Why: these reduce the pressure that forces the gate open. Limitations: they work only if done — half-done, they half-work.
Step 2: Medicine — precise, not indefinite
What: PPIs (omeprazole, pantoprazole, rabeprazole, esomeprazole) taken 30–60 minutes before breakfast — highly effective at healing oesophagitis; H2 blockers (famotidine) for night-time breakthrough; antacids/alginates for immediate relief; prokinetics where emptying is slow. Why: control acid while the pipe heals. Limitations: long-term use deserves annual review — the goal is the lowest effective dose, not lifetime default.
Step 3: Surgery — the durable cure
What: laparoscopic Nissen fundoplication — keyhole surgery that wraps the upper stomach around the lower oesophagus to rebuild the barrier; 1–2 day stay; 90–95% symptom-free at 10 years. The LINX magnetic sphincter is an alternative that preserves normal swallowing. Why/when: large hiatus hernia, medicine dependence, or PPI failure. Limitations: needs proper work-up (endoscopy, manometry) and an experienced team.
Barrett's surveillance — if diagnosed
What: scheduled endoscopy — every 3–5 years for non-dysplastic Barrett's; every 6–12 months or radiofrequency ablation for low-grade dysplasia; EMR or surgery for high-grade. Why: it is the safety net that makes Barrett's manageable rather than frightening.
What happens after diagnosis — the usual pathway
- Symptoms assessed — heart is cleared first when chest pain is involved
- Endoscopy documents the oesophagus — damage graded, Barrett's excluded
- Defined PPI course + mechanics plan — healing window, target weight, meal timing
- Review — symptoms controlled? Dose reduced stepwise
- Advanced testing where needed — pH study, manometry
- Surgical discussion — for medicine dependence, hernia or failure
- Surveillance — Barrett's patients on a scheduled endoscopy programme
What is the outlook?
Genuinely good — provided you treat it as the disease it is. Most patients reach excellent control with the right lifestyle structure and a properly defined medicine course. For those seeking freedom from daily tablets, fundoplication offers a durable, evidence-backed cure. And for the minority with Barrett's, surveillance turns a frightening word into a managed routine. The poor outcomes in GERD belong almost entirely to people who never investigate and never treat.
Nutrition and daily life
Meal timing beats meal content
The single most effective habit: nothing within 3 hours of bedtime. A smaller dinner at 7 pm beats a perfect dinner at 10.
Trigger mapping
Coffee, alcohol, spicy and fried food, chocolate, mint, citrus, carbonated drinks — your triggers are personal. Keep a simple week's diary; our team turns it into your personalised avoid-list.
Sleep mechanics
Raise the head of the bed 15–20 cm (blocks under the legs, not extra pillows — pillows fold the stomach). Left-side sleeping helps many patients.
Weight — the honest paragraph
Weight around the waist is pressure directly on the valve. Even a 5–10% reduction changes the disease. This is not about appearance; it is mechanics.
Questions to ask your doctor
- Do I need an endoscopy — or is a structured medicine trial right for me first?
- Is there any visible damage — oesophagitis, stricture, or Barrett's?
- What is my defined medicine course — and what is the exit plan from daily PPIs?
- Which of my habits are driving this — can you help me prioritise two?
- Am I a candidate for fundoplication — and what would the work-up involve?
- What are the real risks of long-term PPIs for me?
- If Barrett's is found, what is my surveillance schedule?
If you would like more confidence about your diagnosis or treatment plan, seeking a second opinion is reasonable.
Frequently Asked Questions
Is GERD a lifelong condition?
GERD is a chronic condition requiring ongoing management. With lifestyle changes and medical therapy, most patients achieve good symptom control. Surgical fundoplication can provide a long-term cure, eliminating the need for daily medication in most patients.
Are PPIs safe for long-term use?
PPIs are generally safe for most people. Long-term concerns include mild reductions in magnesium and calcium absorption, and possible small increases in C. difficile risk. Annual review with your doctor is recommended — and the risk of untreated GERD (Barrett's, cancer) far outweighs the risks of appropriately dosed PPIs.
Does GERD cause cancer?
GERD leading to Barrett's oesophagus and then cancer is a possible but not inevitable pathway. Only about 0.3% per year of Barrett's patients develop oesophageal cancer. Treating GERD and surveillance for Barrett's significantly reduces cancer risk.
Can GERD be cured permanently without tablets?
Yes, in selected patients. Laparoscopic fundoplication rebuilds the anti-reflux barrier and frees most patients from daily medication. For others, disciplined lifestyle correction allows safe dose reduction. The right answer depends on your endoscopy findings and body habitus.
Is it safe to take PPIs (omeprazole, pantoprazole) for years?
Long-term unsupervised use has recognised associations — B12 and magnesium deficiency, fracture risk, kidney effects and masking of oesophageal disease. We aim for the lowest effective dose after documenting your oesophagus with endoscopy.
What is Barrett's oesophagus and who needs surveillance?
Barrett's is a pre-cancerous change of the lower food-pipe lining caused by years of acid exposure. It is diagnosed by biopsy during endoscopy. Patients with it need periodic surveillance endoscopy — typically every 3–5 years depending on findings.
Is my chest pain reflux or a heart problem?
Never assume. Cardiac causes must be excluded first — especially with exertional pain, diabetes or age over 40. Once the heart is cleared, we evaluate the oesophagus. When in doubt, go to an emergency room first.
Which daily habits worsen GERD most?
Late dinners within 2–3 hours of bedtime, large fatty meals, carbonated drinks, smoking, alcohol, tight waistbands and lying flat. Fixing these alone relieves many patients — our team gives you a personalised version of this list.
How Dhaara Speciality Hospital can help
And if you need us, here is what stands ready for you under one roof in Yelahanka, Bangalore:
- The Dhaara reflux protocol — document with endoscopy, treat with the right PPI course, fix the mechanics, review
- 24-hour pH-impedance and manometry — objective evidence before big decisions
- Laparoscopic fundoplication — keyhole anti-reflux surgery with 1–2 day stay, see laparoscopic surgery
- Barrett's surveillance programme — scheduled, systematic, unhurried
- Dietician support — see Nutrition & Dietetics
- 24/7 emergency and critical care

Dr. Srinivas Bojanapu
MBBS, MS, FACRSI, DrNB, PDF — Surgical Gastroenterologist & HPB Surgeon with 16+ years of experience and 5,000+ procedures.
Medically reviewed by Dr. Srinivas Bojanapu — MBBS, MS, FACRSI, DrNB, PDF · Surgical Gastroenterologist & HPB Surgeon · Last updated: September 2026.
This page provides general information and is not a substitute for personal medical advice, diagnosis or treatment. Treatment decisions are always individualised after clinical assessment.
Sources & standards:
- Institutional figures on this page (patients treated, fundoplication outcomes) are based on Dhaara Hospital records and published surgical literature.
- GERD and Barrett's management follows internationally accepted clinical guidance.
Book Your Consultation
Still reaching for the antacid bottle? Get a proper diagnosis — and a plan that ends, not manages — at Dhaara Speciality Hospital, Yelahanka.
Words From Our Happy Clients
Glowing testimonials from satisfied clients share their positive experiences.
Dhaara Speciality Hospital is a trusted healthcare institution equipped with state-of-the-art facilities and a team of skilled surgeons, including specialists in laparoscopic procedures. Choosing Dhaara for your laparoscopic gallbladder surgery comes with several advantages.
More Reviews
Vinay T
India
Surprised at the excellent facilities
I visited Dhaara Hospital and consulted with Dr. Prathima, a fantastic gynecologist. She's professional, friendly, and listens to my concerns. Her treatment worked well for me, and she always suggests the best.
Suchetha
India
Surprised at the excellent facilities
Dr Sreenivas is brilliant. The way, he listens to the patients issue giving so much time inspite of his busy schedule. I am very happy to have met him for my mom's surgery. Best Gastro surgeon👏👏.

.webp)
.webp)

